


by Joshua Scarselli.
Today I got to sit down with Dr. Elise De. Dr. De uses her medical knowledge to run a YouTube channel dedicated to various urological and pelvic health concerns, including UTIs, pain, catheters, and diagnostics. Dr. De headed up a team that conducted the largest of its kind study into recurrent urinary tract infection-related deaths being reduced through the use of vaginal estrogen. Her team’s research is being featured in an article gracing the cover of USA Today on Wednesday, September 30.
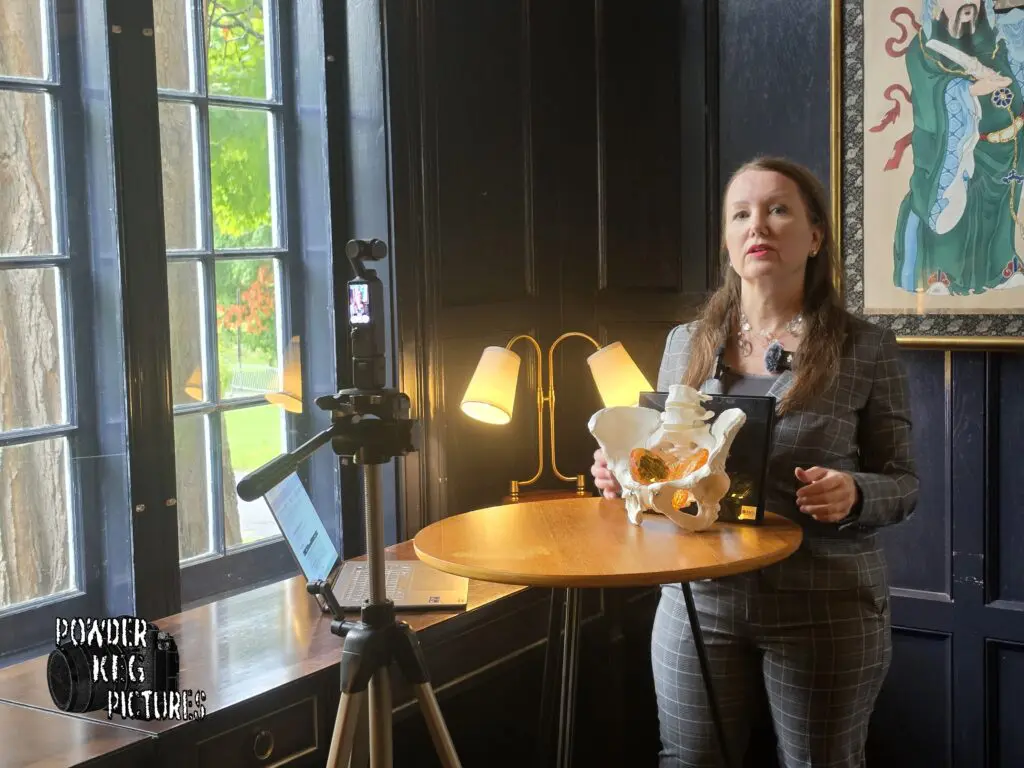
RRX: First I want to start talking about your YouTube channel. How did you decide to take your medical experience and put it on YouTube? What drove you to that?
ED: So I find that people have a really hard time getting what they need from the fragmented healthcare system, even if they have the best doctors. People with pelvic health issues have multidisciplinary needs, so they may need neurologists, urologists, gynecologists, or pelvic floor physical therapists. For example, someone who has lower urinary tract symptoms and is not getting better — we may eventually find out they have MS. That’s a reasonably common story that we all think about. If the patient is educated to ask the correct questions, we may find it earlier. And there are plenty of other diagnoses. If you’re only looking at it from the lens of your specialty, you’re not necessarily going to come up with a diagnosis. Like a hip problem causing pelvic pain. I really wanted that information to be direct to patients. Or simple education, like a voiding diary. Physicians just don’t have time to go through all of the education needed, so having it recorded gives a resource to my practice, my partners, my colleagues within medicine, and patients who are too far away to see our practice. If the information is useful, we want them to have it.
RRX: How have you taken your YouTube channel and used it to help educate future doctors?
ED: So we use it for things like the catheter education videos on my YouTube channel. But this all started through the International Continence Society starting over a decade ago. I was on the Education Committee, and there we created something called ICS TV, International Continence Society TV. We filmed, archived, organized, curated all that, you know, really gold-standard content for the International Continence Society. At the same time that we were setting the standards for the Western world, we used this platform to create fistula education that reached every corner of Africa and other high-prevalence regions. For free. The Internet is an amazing thing. The ICS is a very multidisciplinary organization. There was a significant interest in understanding pelvic pain. The ICS supported us in creating a full 24 hours of expert pelvic pain education, and that’s all edited and curated on the ICS TV website by our Albany Med gap year pre-med student, Christine Cui. The link is below.
RRX: So coming up, you have a big article in USA Today. Can you tell us how you got involved with that?
ED: Yes, we know that vaginal estrogen prevents recurrent urinary tract infections. That is in the American Urological Association guidelines. So with Justin LaClaire, an Albany Med fourth-year medical student from Delmar who’s applying to urology; Joseph Visingardi, who was a local pharmacist and medical student at Albany and is now a dermatology resident in Rochester; Paul Feustel, our statistician at Albany; Brennan Wells, who was a visiting student at Albany; and Joe Deckert, who works for Epic Healthcare Systems in Verona, Wisconsin, we used the Cosmos Epic Database. This is a database that has 300 million de-identified medical records, and you can make very powerful correlations. We found 1.8 million women with recurrent urinary tract infection of all ages. We compared those who were and were not on vaginal estrogen. The meat of the article is that the rates of sepsis, hospitalization, and death in those prescribed vaginal estrogen were a fraction of those who were not.
We can’t be sure they took it, so it could be an indicator of bias toward simply more creative medical care, but the signal is so strong we cannot ignore it. The USA Today article cites that data, and it also tells a story of women who’ve died from recurrent urinary tract infection.
You should know it is rare to die of a recurrent urinary tract infection, so we don’t want to cause panic, but it happens. I especially worry about it in my patients who have complex anatomy, high-pressure bladder, reflux up to the kidneys, and more than simply genital urinary syndrome of menopause, contributing to the UTIs. In our article, we found that only a small percentage of women who should be on vaginal estrogen for recurrent urinary tract infections have been prescribed this treatment.
RRX: How did USA Today approach you about the article?
ED: So Rachel Rubin, who is an incredible urologist who’s a real advocate for women’s health, put me together with Laura Trujillo of USA Today. We both contributed to the article, along with some other amazing physicians and commentators. Rachel Rubin is openly vocal about this subject because she almost lost her mother to a UTI. She recommended USA Today cite the publication. Many of us were excited to see the statistics on the day that we all knew were true. Vaginal estrogen saves lives.
So Rachel Rubin put us together, and Justin and I spoke with Laura Trujillo back in July, when the publication came out, and USA Today did their own research, really looking into the data behind these deaths. I was really impressed with Laura Trujillo’s ability to tell the story of these women and also that of the data behind it. She really did her research.
RRX: The article says that your study was the largest of its kind. Can you tell us what it’s like to know you’ve done the largest of its kind study and that it’s having so much of an impact that a national publication picked it up?
ED: Well, that’s the beauty of big data. You know, you pick up on things that show really large trends in medicine. It’s more than just, you know, your own theory about what you’re doing for your patient; you can really verify some of the things that are in the guidelines and some of the things you know from clinical experience. I think at this stage in my career, anything that I am doing on an academic level is really thinking about how it can change outcomes for more people than I can see in clinic. It is how we can really improve healthcare, train the brilliant people who follow us, and empower patients living the experience directly. This article is hopefully going to be very gratifying.
What is really fun is that the Argus Hotel here in Albany, where we are doing our interview today, was very welcoming in letting us have space to hold meetings after clinical hours when we had time to review and go over findings.
RRX: Do you have any videos coming up that we should look out for?
ED: We’re always putting videos on YouTube. For example, skills for people who are placing catheters, to prevent injury to their patients. We create videos for providers, and we also create videos for patients who are dealing with refractory, chronic pelvic pain, interstitial cystitis. Patients who are scheduled for urology procedures like a uroflow, cystoscopy, urodynamics; most of the videos are useful to both patients and to providers. Like “Causes of Pelvic Pain”; most of the videos are reasonably short, 5 to 10 minutes. They will refer to greater resources, like the www.icsTV/PelvicPain series for providers who really want to learn about pelvic pain. Also, the patients who might go to the facingpelvicpain.org website and find links to organizations for more specific deeper dives into subject matter.
RRX: Is there anything you want to add?
ED: I think it’s really helpful for patients to be educated and also to use the digital tools at our disposal. So for people who are seeing a physician, when there’s a portal that you can sign up for, for example, MyChart in Epic, it’s really helpful to be signed up so that you can read your notes and see your test results in real time. You can also link your MyChart accounts with different healthcare systems.
You can ask your sister, mother, daughter, or brother to be a proxy on your chart. If you are unwell, they can have access to your chart. I have access to both of my parents’ charts. I haven’t had to use it yet because they’re both well and they manage their own health, but at the time that they need me, I now have access to seamlessly take charge of whatever their needs are.
Another thing that people can do when they have a complex medical situation, after removing all of their identifying information, is copy and paste the information into large language models such as Claude or ChatGPT and ask them, “What should I be worried about? What should I be asking my doctor?” This runs the risk of a confidentiality violation, and it is certainly not medical advice, so it is very important to carefully remove any identifying data and to use it as a question-generating platform rather than question answering.

